Hair Transplant Graft Survival: What the Number Really Tells You
Clinically reviewed by Dr. Gaurav Solanki, MDS, Oral and Maxillofacial Surgeon, on .
A useful graft-survival claim explains what was counted, how it was counted and when the result was assessed. A photograph can show a cosmetic change. On its own, it cannot tell you what proportion of the transplanted grafts survived.
Before comparing percentages, ask to see the definition behind the number. Does it refer to grafts, individual hairs, a measured patch of scalp or a clinician’s overall impression? Those answers determine whether two figures describe the same outcome.
Grafts, hairs, density and coverage describe different things
A graft is a small piece of tissue containing one or more hair follicles. A graft count records the tissue units transplanted; a hair count records individual hairs. A report should say which unit it uses rather than treating the terms as interchangeable.
Density is a count within a defined area. Coverage describes how much scalp appears concealed. A density measurement needs an area and a counting method. A coverage photograph also depends on how the hair and scalp are presented.
Consider the question, “How many grafts survived?” To answer it with a percentage, the starting count and follow-up count must use a compatible definition. Counting all visible hairs in a later photograph does not automatically separate transplanted hair from hair that was already there.
This distinction also matters when reading research. A study measuring hairs per square centimetre is answering a different question from an experiment testing cells in grafts outside the body. Neither should be relabelled as a clinic’s independently measured survival rate.
What happens between extraction and implantation?
Hair transplantation involves removing grafts from a donor area, holding and handling them outside the body, and placing them into prepared recipient sites. Research on preservation methods investigates parts of this process. It does not make every method interchangeable or establish one outcome for every patient.
For example, Gho and Neumann studied small grafts from three patients using a laboratory staining test after storage in different solutions. The experiment assessed viability outside the body. It did not measure a final clinical hair-growth percentage after transplantation. Its specialised graft technique also limits direct application to other procedures. Read the original preservation-solution study.
A separate pilot randomised study by Pathania and colleagues compared platelet-rich plasma with Ringer’s lactate as a holding solution in 20 men. It assessed growth and density through six months, using two-week postoperative density as its reference; participants also received minoxidil. The small sample, protocol and measurement choices matter. This study does not establish that another clinic uses the same protocol or achieves the same results. Read the primary holding-solution trial.
For a patient, the practical question is how the proposed procedure is organised and documented. Ask who is responsible for each stage, what handling information is recorded and how the team evaluates growth afterwards. A brand name or a statement that grafts are handled carefully is not a substitute for that explanation.
Who performs each stage at Cult Aesthetics?
The clinic-confirmed division of work is:
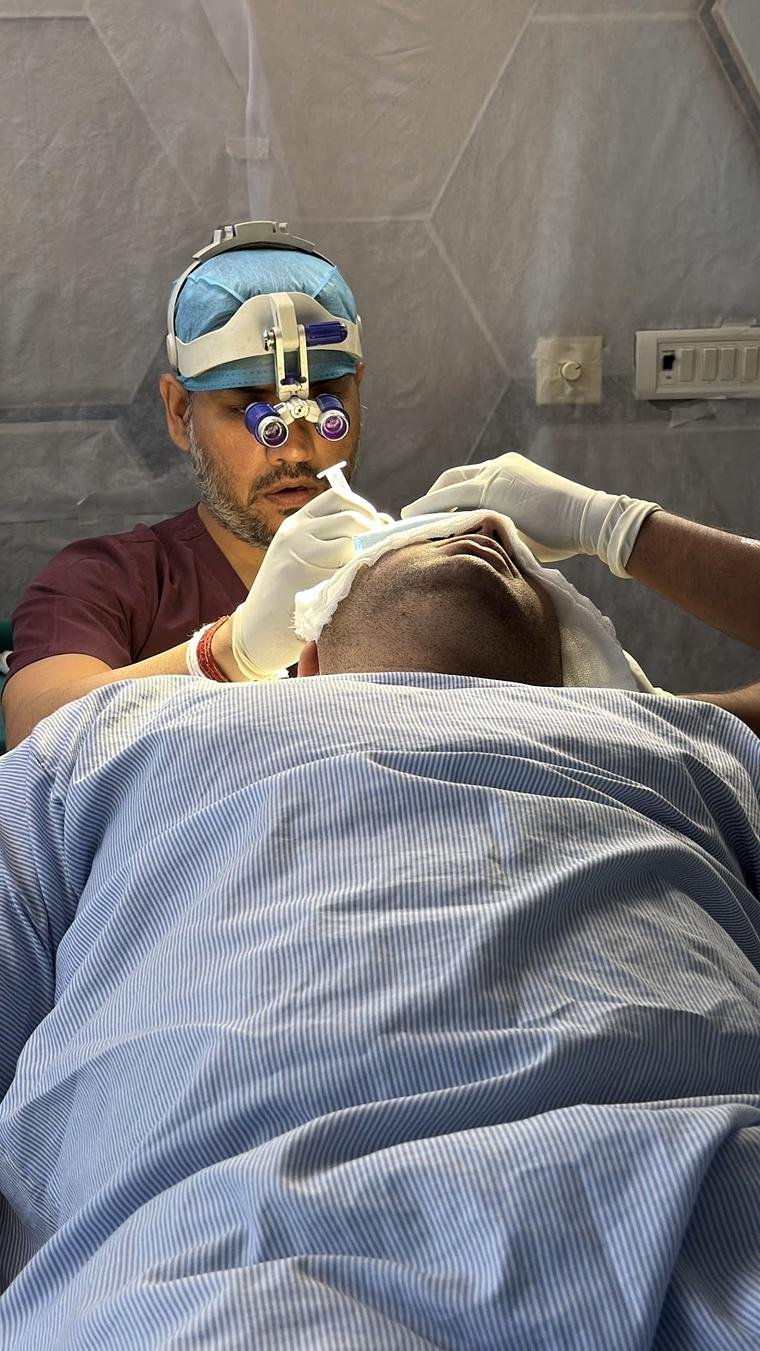
- Dr. Gaurav Solanki, MDS, Oral and Maxillofacial Surgeon, performs hairline design and marking, graft extraction and recipient-site slit creation using a sapphire blade.
- Technicians perform forceps-based implantation, described by the clinic as no-touch implantation.
Forceps-based implantation should not be described as Choi-pen implantation. The term “no-touch” also needs a clear explanation of the handling technique; it does not, by itself, establish a measured survival advantage.
This role map describes who does the work. It makes no claim that the doctor personally implants every graft, and it is not evidence of a particular success percentage. The 2021 Hair Transplant Practice Guidelines recommend explaining the surgeon’s and assistants’ roles. They are general practice recommendations, not an audit of this clinic. Read the practice guideline.
Six questions behind a graft-survival percentage
1. What is the starting count?
Ask whether the denominator is grafts extracted, grafts judged suitable for placement, grafts implanted or individual hairs. Ask how that count was recorded. If the starting number changes between documents, request an explanation before comparing it with a later result.
2. What was counted at follow-up?
Was growth counted in marked sample areas, measured across the treated area or assessed visually? Ask how native hair was distinguished from transplanted hair and whether the same area was examined each time. A sample-area estimate should be described as an estimate.
3. When was it assessed?
Look for the operation date and the date of assessment. A day-of-surgery image documents placement. Later images document appearance at their stated time points. A study’s chosen follow-up date should not be turned into a universal deadline for every individual’s result.
4. What else happened during follow-up?
Ask whether the patient had another procedure or used other hair-loss treatments. If several interventions occurred, an improvement in overall appearance cannot automatically be attributed to graft survival alone. The case history should make those interventions visible.
5. Who measured the outcome?
A patient’s satisfaction, a treating clinician’s assessment and an independent assessment can each be useful. They should be identified accurately. Ask whether the assessor used a consistent counting method and whether an external audit actually occurred.
6. Whose outcomes are included?
One selected case cannot describe the full range of a clinic’s outcomes. If a clinic gives a practice-wide figure, ask how many patients were eligible, how many were assessed and what happened to patients without follow-up. A result based only on those who returned needs that limitation stated.
Why a fuller-looking result cannot answer every question
A before-and-after comparison can be useful without being a graft-survival calculation. It may help you discuss the hairline, the distribution of visible hair or the appearance of the donor area. Its limits should remain clear.
For example, if the later photograph uses longer hair and a different angle, you can still view the case. You cannot assume that all of the visible difference came from a higher follicle count. Request comparable views and the recorded treatment details rather than guessing a percentage.
Likewise, a thin-looking photograph does not identify the cause. It cannot, by itself, distinguish a counting problem, a change in existing hair, a photographic difference or an issue requiring clinical assessment. If you are concerned about your own progress, contact your treating clinician rather than using an online image to diagnose graft failure.
Quick answers: what does hair-transplant success rate mean?
A percentage is interpretable only when the outcome, starting count, measurement method and follow-up point are stated. Graft survival and a satisfactory cosmetic result describe different things. The questions below summarise the evidence distinctions explained in this article.
Is graft survival the same as visible hair density?
No. A graft is not necessarily one hair, and a density measurement describes a particular area. Visible coverage is another outcome again. Ask which measure the figure represents before comparing it with a photograph or another reported result.
Can before-and-after photographs prove a survival percentage?
Photographs can document appearance, but they do not by themselves supply the starting graft count or a follow-up counting method. Lighting, angle and hair length also matter when comparing appearance. Ask for the measurement record behind a numerical claim.
Can two clinics’ success rates be compared?
Start by checking whether they use the same definition of success. Then compare the denominator, assessment method, follow-up interval and which patients were included. If these are missing or different, the percentages do not establish a reliable ranking.
Does a published study prove a clinic achieves the same result?
No. The study’s participants, methods and setting matter. Laboratory viability is not the same measurement as clinical growth, and a study of a particular preservation protocol does not establish that another clinic used it or achieved the same outcome.
What should I ask when someone quotes a success rate?
Ask: “What exactly was counted, what was the starting number, when was the result measured, who measured it, and were patients without follow-up included?” The answers make the claim more useful than the percentage alone.
If the percentage comes from a chatbot summary, use this guide to checking AI answers about hair loss to trace the claim to its source.
Question-and-answer summary added 19 October 2026. This section restates the evidence distinctions above; it does not introduce a new outcome estimate or represent a new clinical review.
Bring this short checklist to a consultation
- What does the proposed graft count mean, and how will it be documented?
- Who performs extraction, recipient-site creation and implantation?
- How are growth and appearance assessed at follow-up?
- If a percentage is quoted, what are its source, denominator, method and follow-up date?
- What limits of donor supply and coverage apply to this particular plan?
- What would prompt a further examination rather than reassurance from photographs alone?
Keep the answers with your consultation notes. They provide a more useful basis for comparison than an unexplained percentage.
Related reading and consultation
For planning questions, read Cult’s guide to hair-transplant density planning. For reasons to delay or reconsider surgery, see when a hair transplant may not be the right next step. The clinic’s procedure-role page explains its service model.
You can request an individual consultation to discuss your records, donor assessment and proposed plan. This article provides general education and does not determine suitability or predict an individual’s result.
Watch: what graft survival looks like in practice
Dr Gaurav Solanki on why transplants fail — and what a corrected case involves.
“As a doctor I evaluated clinics across Delhi NCR for three months before choosing Dr. Gaurav Solanki for my Grade-5 case. At 10 months the result is completely natural — colleagues assume it is my own hair. The predictability of the outcome is what I value most.”
“Since 8 months from my hair transplant, results are good and more improvement is expected. Doctor and staff were cooperative in every aspect — I can call or chat any time.”
“Got my hair transplant done at Cult Aesthetics by Dr. Gaurav Solanki and I am extremely happy. The team was very professional and the results look absolutely natural.”